 Wednesday, November 18, 2026
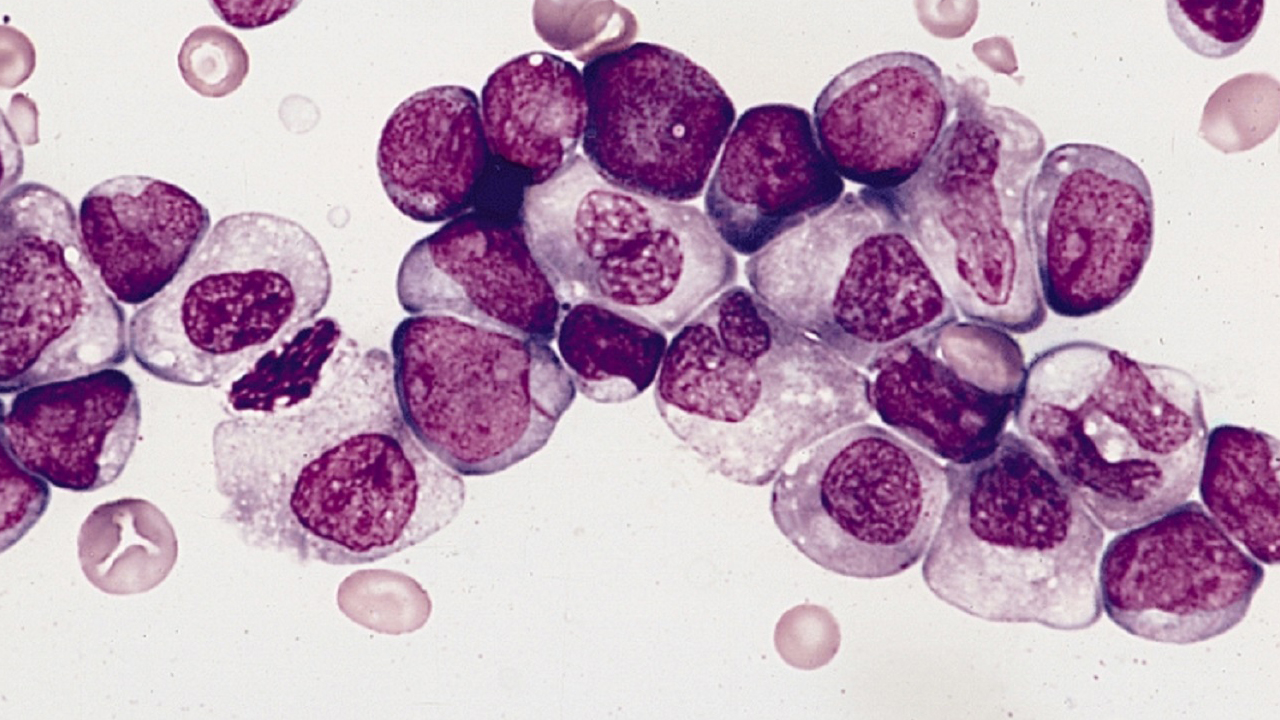
 Acute myeloid leukemia is one of the most aggressive and difficult-to-treat blood cancers with a very low survival rate





AbbVie recently announced that the U.S. Food and Drug Administration (FDA) has provided full approval to VENCLEXTA (venetoclax) in combination with azacitidine, or decitabine, or low-dose cytarabine (LDAC) for the treatment of newly-diagnosed acute myeloid leukemia (AML) in adults who are age 75 years or older, or who have comorbidities that preclude the use of intensive induction chemotherapy. The approval is supported by data from the Phase 3 VIALE-A (M15-656) and VIALE-C (M16-043) studies and updated data from the Phase 1b M14-358 and the Phase 1/2 M14-387 studies. The FDA previously granted accelerated approval to VENCLEXTA for this indication in 2018.
"AML is a complex and challenging disease with generally low survival rates. This approval is significant because data from our VIALE-A trial has shown that newly-diagnosed patients, who cannot undergo intensive chemotherapy, lived longer when treated with VENCLEXTA plus azacitidine than those treated with azacitidine alone," said Mohamed Zaki, M.D., Ph.D., vice president and global head of oncology development, AbbVie. "This trial also provides physicians more information for managing patients - from treatment initiation, to assessing response and management post disease remission."
Positive overall survival (OS) data seen at an interim analysis of the VIALE-A trial led to an early submission supporting the FDA approval of VENCLEXTA in AML. The trial showed patients on the active regimen of VENCLEXTA plus azacitidine achieved a 34% reduction in the risk of death compared to azacitidine in combination with placebo (Hazard Ratio [HR]=0.66 [95% CI: 0.52-0.85], p<0.001). The median OS for patients in the VENCLEXTA arm was 14.7 months (95% CI: 11.9, 18.7) versus 9.6 months in the placebo arm (95% CI: 7.4, 12.7). Additionally, patients in the VENCLEXTA plus azacitidine arm achieved a complete remission (CR) rate of 37% (95% CI: 31%, 43%) with a median duration of CR of 18.0 months (95% CI: 15.3, -) compared with patients in the placebo plus azacitidine arm with a CR rate of 18% (95% CI: 12%, 25%) with a median duration of CR of 13.4 months (95% CI: 8.7, 17.6). The observed safety profile was generally consistent with the known safety profile of VENCLEXTA in combination with azacitidine. For patients taking VENCLEXTA in combination with azacitidine, the most frequent serious adverse reactions (ARs; ≥5%) at first use were febrile neutropenia (30%), pneumonia (22%), sepsis (excluding fungal; 19%) and hemorrhage (6%).1,6
Data from VIALE-A was presented for the first time as a late-breaking abstract at the 25th European Hematology Association (EHA) Annual Congress in June 2020 and recently published in the New England Journal of Medicine.
"For far too long, people with AML had very few treatment options, aside from very intense chemotherapy. Today's news continues the progress of bringing more treatment options to patients with this devastating disease," said Lee Greenberger, Ph.D., chief scientific officer of The Leukemia & Lymphoma Society.
Data from the VIALE-C trial was presented at both the 2020 American Society of Clinical Oncology (ASCO) Annual Meeting and the EHA Annual Congress and previously published in Blood.8 The median OS for VENCLEXTA in combination with LDAC was 7.2 months (95% CI: 5.6, 10.1) and 4.1 months for LDAC in combination with placebo (95% CI: 3.1, 8.8). The HR for the primary endpoint of OS was 0.75 (95% CI: 0.52-1.07; p=0.114). The trial did not meet its primary endpoint of statistically significant improvement of OS for patients with AML who are ineligible for intensive chemotherapy at the time of the planned analysis. Efficacy was based on the rate of CR and duration of CR with supportive evidence of rate of CR + complete remission with partial hematologic recovery (CR+CRh), duration of CR+CRh, and the rate of conversion from transfusion dependence to transfusion independence. In the VENCLEXTA arm, the most frequent serious ARs were (≥10%) pneumonia (17%), febrile neutropenia (16%) and sepsis (excluding fungal; 12%).
AML is an aggressive and difficult-to-treat blood cancer with a low survival rate. Despite recent advances in available therapies, the five-year survival rate for patients diagnosed with AML remains approximately 29%.10 AML typically worsens quickly, and due to age or comorbidities, not all patients are eligible to receive intensive chemotherapy.
The FDA reviewed the clinical data under the FDA's Real-Time Oncology Review (RTOR) pilot program and Project Orbis initiative, which led to approval in the U.S. in October 2020. Project Orbis provides a framework for concurrent submission and review of oncology drugs among international partners. The U.S. FDA, the Australian Therapeutic Goods Administration, Swissmedic, Health Canada and ANVISA (Agência Nacional de Vigilância Sanitária) collaborated on this review based on the marketing applications submitted in their respective countries.
Venetoclax is being developed by AbbVie and Roche. It is jointly commercialized by AbbVie and Genentech, a member of the Roche Group, in the U.S. and by AbbVie outside of the U.S.





-23-300x250.png)





















