When Rural Women Speak to a Bot: What We Learn About AI in Maternal Care

▴ AI in Maternal Care
A multilingual, voice‑driven chatbot that supports diet tips during pregnancy, early warning signs, postnatal nutrition, or child immunization schedules becomes a lightweight yet powerful companion.

Hello! If you're looking for high-quality genericmedications, fast delivery and excellent customer service, ourstore is the right choice for you. With over 20 years of onlineexperience, we guarantee safe, effective products that are alwaysin stock. Delivery within 48 hours, free shipping from $200, and 100% money-back guarantee if your order doesn't arrive on time.

👉 Order now at BestCheapPills and discover exclusive discounts for registeredcustomers!

In far‑flung villages where internet access is patchy and literacy rates vary, a quiet experiment is reshaping how expectant mothers and frontline workers access health guidance. A recent usability study has focused on how underserved women interact with chatbots designed to deliver maternal and child health information. The findings are surprising, thought‑provoking, and deeply human; they reveal a world where technology can bridge gaps but only if it is built around women’s real lives and language.

Researchers reached out to women who often juggle home, field, family care, and social expectations. When asked, many confirmed they owned or had access to a basic smartphone, and used WhatsApp or calls regularly but rarely for medical advice. That was the moment when a health chatbot seemed promising: a tool available day or night, offering answers in local tongue without judgement.

What emerged from the interviews and discussions was striking: many women valued chatbots, but not in text form. They prized voice‑based interaction and visual cues, over typed answers. Typing a message in Devanagari script or even Hinglish was difficult, especially if one’s schooling had ended early or never begun. But hearing a friendly voice giving advice felt intuitive, respectful, even comforting. They asked questions like “My baby isn’t breastfeeding at night what should I do?” or “Is it normal to feel weak two months after delivery?” There were no medical textbooks here, just lived experiences craving clear, non‑judgemental answers.

This reinforces a vital truth about digital health tools: they succeed only when they fit into women’s daily routines and constraints. Many rural women are only free during breaks in domestic work. A long questionnaire or complex navigation feels burdensome, whereas a quick voice prompt via a chatbot can be squeezed into a lull. The study recorded comments that mothers preferred a quick voice chat over navigating menus or typing.

The usability study uncovered deeper layers. Many women saw health chatbots as a reliable supplement, especially when Anganwadi centres or local clinics felt distant or judgmental. Some said they trusted the bot more than family or neighbours, especially on sensitive topics like child spacing, diet in pregnancy, or postnatal warning signs. The privacy of digital advice mattered more than convenience; women appreciated that they didn’t need to shame or seek permission to ask a question.

Of course, there were gaps. The bots struggled with dialects, audio clarity, medical jargon, or cultural sensitivity especially around reproductive health topics that are taboo. Some women asked: “Why won’t the bot talk about menstruation or postpartum bleeding?” And researchers accepted that chatbots must learn cultural context. Technical accuracy alone won’t suffice if the tone feels alien or judgmental.

ASHAs (Accredited Social Health Activists) India’s frontline women health workers were also part of the evaluation. Many found chatbots a helpful backup when they couldn’t recall a protocol. One ASHA from Rajasthan reportedly used a WhatsApp‑based chatbot in Hindi to guide a mother through feeding practices after spotting a low‑weight infant. The chatbot suggested feeding frequency, counselling tips, and flagged possible anemia. The ASHA credited the tool with giving her confidence and clarity and saving time in searching physical registers.

But perhaps the most revealing insight from the usability study was this: time poverty. Women often said, "Who has time to chat when there’s cooking, cleaning, caring?" Their days are relentless. To gain trust, the chatbot had to feel faster and lighter than traditional advice options. The best tools learned to anticipate dropoffs and pivot into voice nudge calls, just like how maternal messaging programs used AI to send reminders to women at risk of disengagement. That behavioral insight improved both listenership and health outcomes in some programs.

This reflects earlier findings from voice‑based AI models designed to call women at risk of missing iron‑folic acid doses or antenatal visits. When the call reached the right time and tone, uptake increased. Similarly, in chatbot design, the key isn't just the answer, it’s recognising when a user is about to quit, not to force features, but to nudge gently, respectfully.

The study also noted that chatbots must mirror local colloquialisms and respect cultural taboos. When women asked about breastfeeding duration or menstrual return, they were frustrated if the bot offered generic answers or avoided the issue. Researchers emphasised co‑development with women themselves meaning these tools are built with real users, not just for them. ASHAs and mothers contributed Q&A libraries, helped form voice tones, and tested prototypes before anything went live.

The implications for maternal and child health are profound. India still faces preventable maternal mortality linked to anemia, hypertension, delayed prenatal visits, or postpartum ignorance. Digital diaries or paper register alone won’t solve it. But a chatbot that can remind, explain, empower, and adapt could help fill those gaps if built for those who need it most.

It’s also a digital equity moment. Many rural women neglect health apps because they feel complex, inaccessible, or irrelevant. But a multilingual, voice‑driven chatbot that supports diet tips during pregnancy, early warning signs, postnatal nutrition, or child immunization schedules becomes a lightweight yet powerful companion. It doesn’t require high-end phones, constant data or perfect literacy. That’s why user‑centric design with underserved women is not idealism it’s essential.

The study also warns developers that success metrics of a health chatbot shouldn’t be limited to number of downloads or bounce rates. It must be measured via trust, perceived usefulness, empowerment, and actual behavior change like increased antenatal visits or iron supplement compliance. A passive app that waits on a shelf accomplishes little.

In the end, what matters most is that the real voices those are often unheard by tech designers are now shaping the design. When a rural mother says, “I need advice but can’t type; I can listen, though,” that is user insight not usually recorded in laboratories but at kitchen hearths and village paths.

What if the future of maternal digital health lies not in the latest AI model but in the art of listening? In that sense, chatbots don’t just deliver information, they learn humanity. And rural India, with its resilience and resourcefulness, can teach the world how to build health tools that serve with empathy, clarity, and cultural warmth.

This usability study reminds us that when underserved women interact with health chatbots, the question isn't whether technology can deliver knowledge. It’s whether it can deliver trust, access, and empowerment and if it can do all that in their own voice.

Tags : #MaternalHealth #HealthyMothers #HealthyBabies #SafeMotherhood #PregnancySupport #SmartMotherhood #TechForGood #InclusiveAI #RuralHealthIndia #DigitalHealthEquity #HealthTrust #HealthTechPolicy #smitakumar #medicircle

Related Stories

Loading Please wait...

-Advertisements-


Trending Now

The Value of Risk Communication in Public HealthOctober 08, 2026
What Makes a Reliable Health Screening Programme?October 08, 2026
How Language Access Can Improve Patient Communication in Indian HealthcareOctober 07, 2026
Why Health Literacy Matters in Preventive HealthcareOctober 07, 2026
Improving Follow-Up After Diagnostic Testing: Where Systems Commonly Break DownOctober 07, 2026
How Community Health Workers Support Preventive Care DeliveryOctober 07, 2026
AI in India's Emergency Departments: Reducing Diagnostic DelaysOctober 06, 2026
AI and Patient Consent in India: Who Is Responsible?October 06, 2026
Wearable Technology in Pregnancy: Benefits and LimitsOctober 06, 2026
Remote Monitoring for High-Risk Pregnancies in IndiaOctober 06, 2026
Fortis Escorts Faridabad Launches ‘Sehat Express’ Mobile Bus for Accessible Doorstep Cancer Screening in association with Faridabad Industries Association Charitable Society and Rotary Club FaridabadOctober 05, 2026
Advanced Thrombectomy Saves 60-Year-Old Woman After Severe Heart Attack at KIMS SaveeraOctober 05, 2026
Constipation, Bloating and Long Sitting Hours: Doctors at RG Hospitals Delhi Warn Urban Professionals Not to Ignore Gut ProblemsOctober 05, 2026
Fermenta – Centre of Excellence for Food Fortification Inaugurated at NIFTEM-T, ThanjavurOctober 05, 2026
Alzheimer’s Dementia: Recognising the Signs, Diagnosing Earlier and Changing the Future of Brain HealthOctober 05, 2026
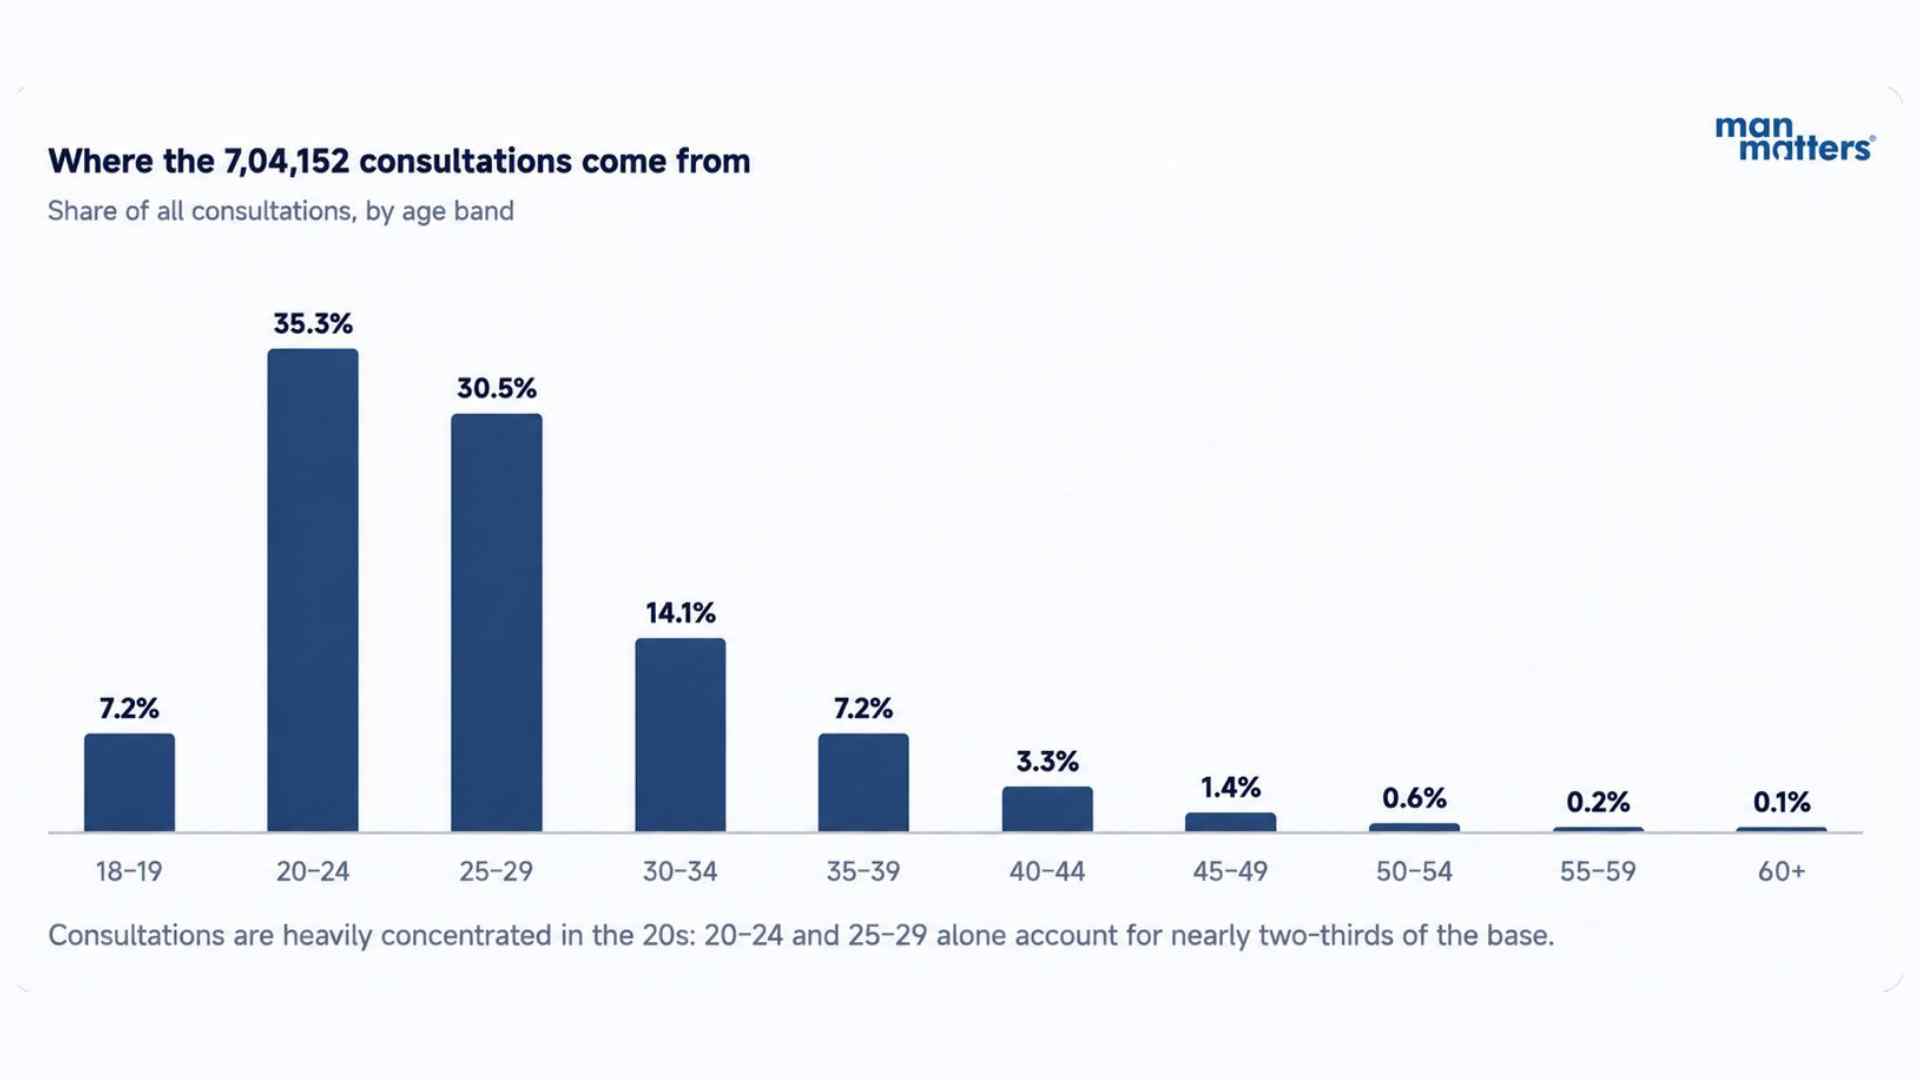
Man Matters Hairfall Case Study 2026: 7 Lakh+ Consultations Reveal How Hair Loss Changes With AgeOctober 05, 2026
Medication Reconciliation: A System-Level Step for Safer Transitions of CareOctober 05, 2026
The Role of Clinical Pharmacists in Safer Medication UseOctober 05, 2026
Nanavati Max Hospital Hosts Max Cancer Congress 2026, Bringing Together Oncology Experts to Explore the Future of Cancer Care October 01, 2026